Introduction
Cardiovascular disease (CVD) is a major cause of
mortality and creates a critical public health burden worldwide
(1). CVD is a complex condition
due to various environmental and genetic factors, and is
particularly more complex in those who have a genetic
predisposition to CVD. In such cases, genetic and hereditary
factors play a major role in the development of CVD (2,3). The
risk of developing CVD involves disorders of the heart and blood
vessels, which includes coronary artery disease (CAD), myocardial
infarction (MI), coronary disease (CD), acute coronary syndrome
(ACS), rheumatic heart disease and other conditions (4). Dyslipidemia plays a crucial role in
the development of CVD. Particularly, decreased levels of
high-density lipoprotein (HDL) cholesterol (5) are highly associated with the
development of all forms of CVD (6). Of note, both environmental and
genetic factors contribute to inter-individual variations in lipid
metabolism and the risk of developing CVD (7).
Apolipoprotein A1 (APOA1) is a key protein
responsible for both the structure and function of the HDL particle
and plays a crucial role in reverse cholesterol transport by
enhancing cholesterol removal from peripheral tissue to the liver
(8,9). The APOA1 gene is located on
chromosome 11q23. APOA1 is associated with the APOA1 serum
concentration and serum levels, which may increase the risk of
developing CVD (10,11). Previous studies have observed that
rs670 has an association with the risk of developing CVD (12). APOA1 is a component of HDL, which
is commonly known as ‘good cholesterol’, although higher HDL
cholesterol levels are epidemiologically associated with a reduced
risk of developing CVD. It has been suggested that increasing the
HDL concentration alone does not protect against CVD, and
highlights the importance of HDL functions (13). APOA1 also contributes to
anti-inflammatory and anti-atherogenic functions; thus, it may
provide protection against atherosclerotic plaque formation
(14).
Among the most commonly studied polymorphisms, the
rs670 (-75 G>A) variant is present in the promoter region of the
APOA1 gene and has been reported to influence transcriptional
activity and circulating HDL level (15). The rs5069 (+83 C>T) polymorphism
is located downstream of the transcription start site and has been
associated with alterations in lipid parameter (16). Several studies have been conducted
across different countries and have examined the association of
these polymorphisms with the outcomes of patients with CVD, such as
CAD, ACS and MI (11,14-16).
Although multiple studies have examined the association between
APOA1 rs670 and rs5069 polymorphism and CVD risk, the findings
remain inconsistent across different populations and study designs.
A previous meta-analysis conducted by Dong et al (12) evaluated the association between
APOA1 rs670 and rs5069 polymorphisms and the risk of developing
CAD. In addition, Xu et al (13) evaluated the association between the
APOA1 rs670 polymorphism and the risk of developing CAD. However,
several studies have been published since then, providing new
evidence regarding the role of these polymorphisms in
cardiovascular disease risk (11,14,17).
Therefore, the present systematic review and meta-analysis was
conducted to systematically evaluate the association between APOA1
rs670 and rs5069 polymorphism with CVD risk, as reported in
eligible case-control studies.
Data and methods
Literature search strategy
A systematic literature search for the present study
was conducted using electronic databases, including PubMed, Web of
Science, Scopus and Google Scholar to identify potentially relevant
studies. The search strategy combined the following key words and
their relevant combinations (APOA1 OR apolipoprotein A1), (rs670 or
-75 G>A, rs5069 or +83 C>T), (cardiovascular disease or CVD,
coronary artery disease or CAD, myocardial infarction or MI, acute
coronary syndrome or ACS, coronary disease or CD). No restriction
was applied based on the year of publication. The eligible studies
identified through the search were published between 1998 to
2026.
A total of ten studies met the inclusion criteria
and were included in the meta-analysis. The methodological quality
of the included case-control studies was assessed using the
Newcastle-Ottawa Scale (NOS) (18). The detailed quality assessment
scores are provided in Table SI.
No language restrictions were applied during the literature search.
However, all the studies that met the inclusion criteria were
published in the English language. The final literature search was
completed on January 30, 2026. The present systematic review is not
prospectively registered in PROSPERO or any other systematic review
registry.
Inclusion criteria
Studies were included if they were case-control
studies, evaluated APOA1 rs670 and rs5069 polymorphisms,
investigated CVD outcomes and included sufficient genotype data.
The methodological quality of the included case-control studies was
assessed using the NOS, evaluated based on the selection of
participants, comparability and exposure.
Exclusion criteria
Studies were excluded in the event that they
included undefined data, were letters, lacked genotype data, or
were review articles. Studies that did not fulfill the inclusion
criteria and studies with duplicate populations were excluded.
Data extraction
Of note, two reviewers had separately carried out
the data extraction using a standardized data extraction form.
Information extracted from each eligible study included first
author detail, year of publication, study region, CVD outcome,
genotyping method and genotype allele frequencies. All selected
articles were carefully reviewed and relevant data were recorded.
Any disagreements between the reviewers were resolved through
discussion. In addition, study quality-related information,
including total sample size, study design and Hardy-Weinberg
equilibrium (HWE) of the control group was also collected. The
process of study selection, and screening and data extraction were
conducted systematically.
Statistical analysis
All the statistical analyses were performed using
the MetaGenyo web tool for genetic association meta-analyses
(19). The level of the
association between APOA1 rs670 and rs5069 polymorphism and CVD
susceptibility was evaluated using odds ratios (ORs) with 95%
confidence intervals (CIs). Pooled ORs were calculated under the
applied genetic models: Allele contrast, dominant, recessive and
over-dominant genotype comparison. The statistical significance of
the pooled effect size was assessed using the Z-test and a
two-sided P-value <0.05 was considered to indicate a
statistically significant difference.
Between-study heterogeneity was evaluated using the
Cochran's Q-test and the magnitude of heterogeneity was quantified
using I2 statistics. Due to the presence of substantial
heterogeneity across the individual studies, the random-effects
model was primarily applied to generate pooled estimates.
Sensitivity analysis was executed by removing one
study at a time to assess the robustness of the pooled result. The
funnel plot was applied to evaluate probable publishing bias,
supported by Egger's regression test, acknowledging the publication
bias test has low statistical power when a small number of studies
are available. HWE in the control group was assessed using
extracted genotype frequency and recorded for each included study
(20).
Results
Included studies and study
characteristics
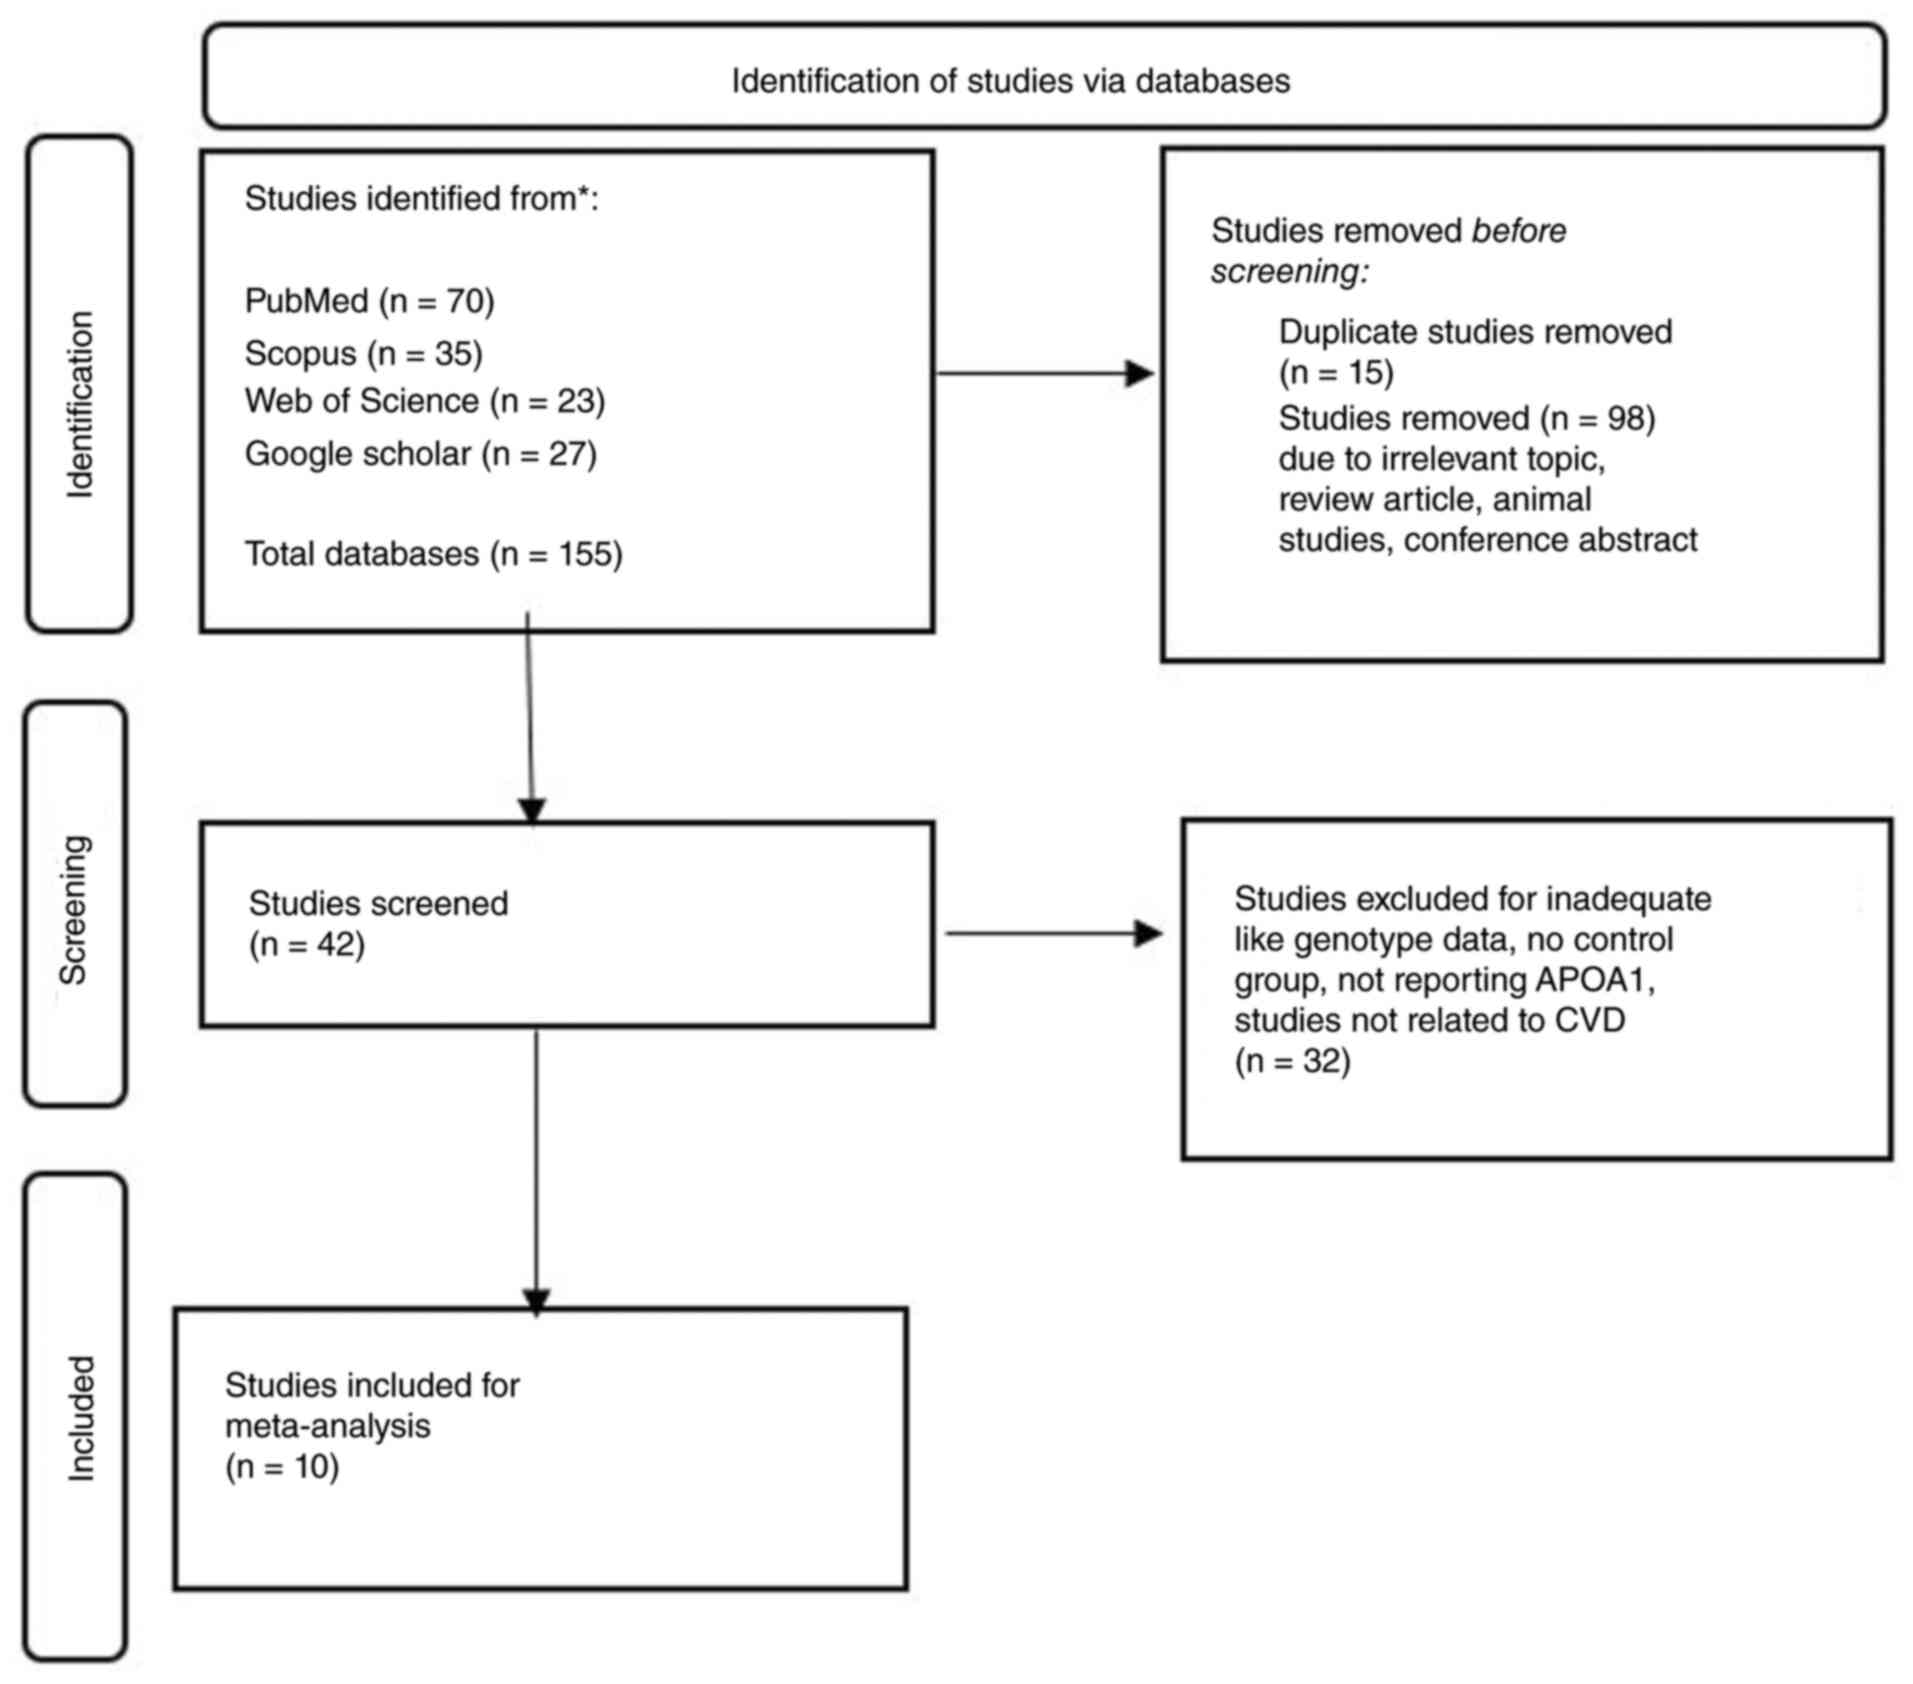
The database research identified 155 records; after
removing duplicates, review articles, meta-analyses, unrelated
articles and animal studies, 42 articles were screened.
Additionally, 32 studies with inadequate information were also
excluded. Following thorough screening, a total of ten studies were
included in the final meta-analysis (3,11,14-17,21).
The process of selecting studies is presented as a PRISMA flow
diagram according to meta-analysis PRISMA guidelines in Fig. 1.
Among the ten selected studies, five studies
described the association of between APOA1 rs670 and the risk of
developing CVD (Table IA)
(3,11,15,16,21)
and five studies described the association between APOA1 rs5069 and
the risk of developing CVD (Table
IB) (11,14,16,17,21).
The methodological quality of the included studies was evaluated
using the NOS. The NOS score ranged from 7 to 8, indicating
moderate to high methodological quality (Table SI).
 | Table ICharacteristics of included studies
for APOA1 rs670 and rs5069 polymorphisms. |
Table I
Characteristics of included studies
for APOA1 rs670 and rs5069 polymorphisms.
| A, Studies on the
rs670 polymorphism |
|---|
| Authors | Year of
publication | Country of the
study | Study design | Outcome | Sample size | Genotyping
method | (Refs.) |
|---|
| Chhabra et
al | 2005 | India | Case-Control | CAD | 370 | PCR | (15) |
| Dawar et
al | 2010 | India | Case-Control | MI | 100 | PCR-RFLP | (16) |
| Liao et
al | 2015 | China | Case-Control | CAD | 600 | PCR-RFLP | (21) |
| Reguero et
al | 1998 | Spain | Case-Control | CD | 176 | PCR | (3) |
| Sohail et
al | 2024 | Pakistan | Case-Control | CAD | 200 | PCR-RFLP | (11) |
| B, Studies on the
rs5069 polymorphism |
| Kumari et
al | 2023 | India | Case-Control | MI | 104 | PCR | (17) |
| Pandith et
al | 2021 | India | Case-Control | ACS | 240 | PCR-RFLP | (14) |
| Liao et
al | 2015 | China | Case-Control | CAD | 300 | PCR-RFLP | (21) |
| Sohail et
al | 2024 | Pakistan | Case-Control | CAD | 200 | PCR-RFLP | (11) |
| Dawar et
al | 2010 | India | Case-Control | MI | 100 | PCR-RFLP | (16) |
Meta-analysis of studies on APOA1
rs670
A total of five studies were included to evaluate
the association between the APOA1 rs670 polymorphism and
susceptibility to CVD and their genotype distributions and HWE
P-values are presented in (Table
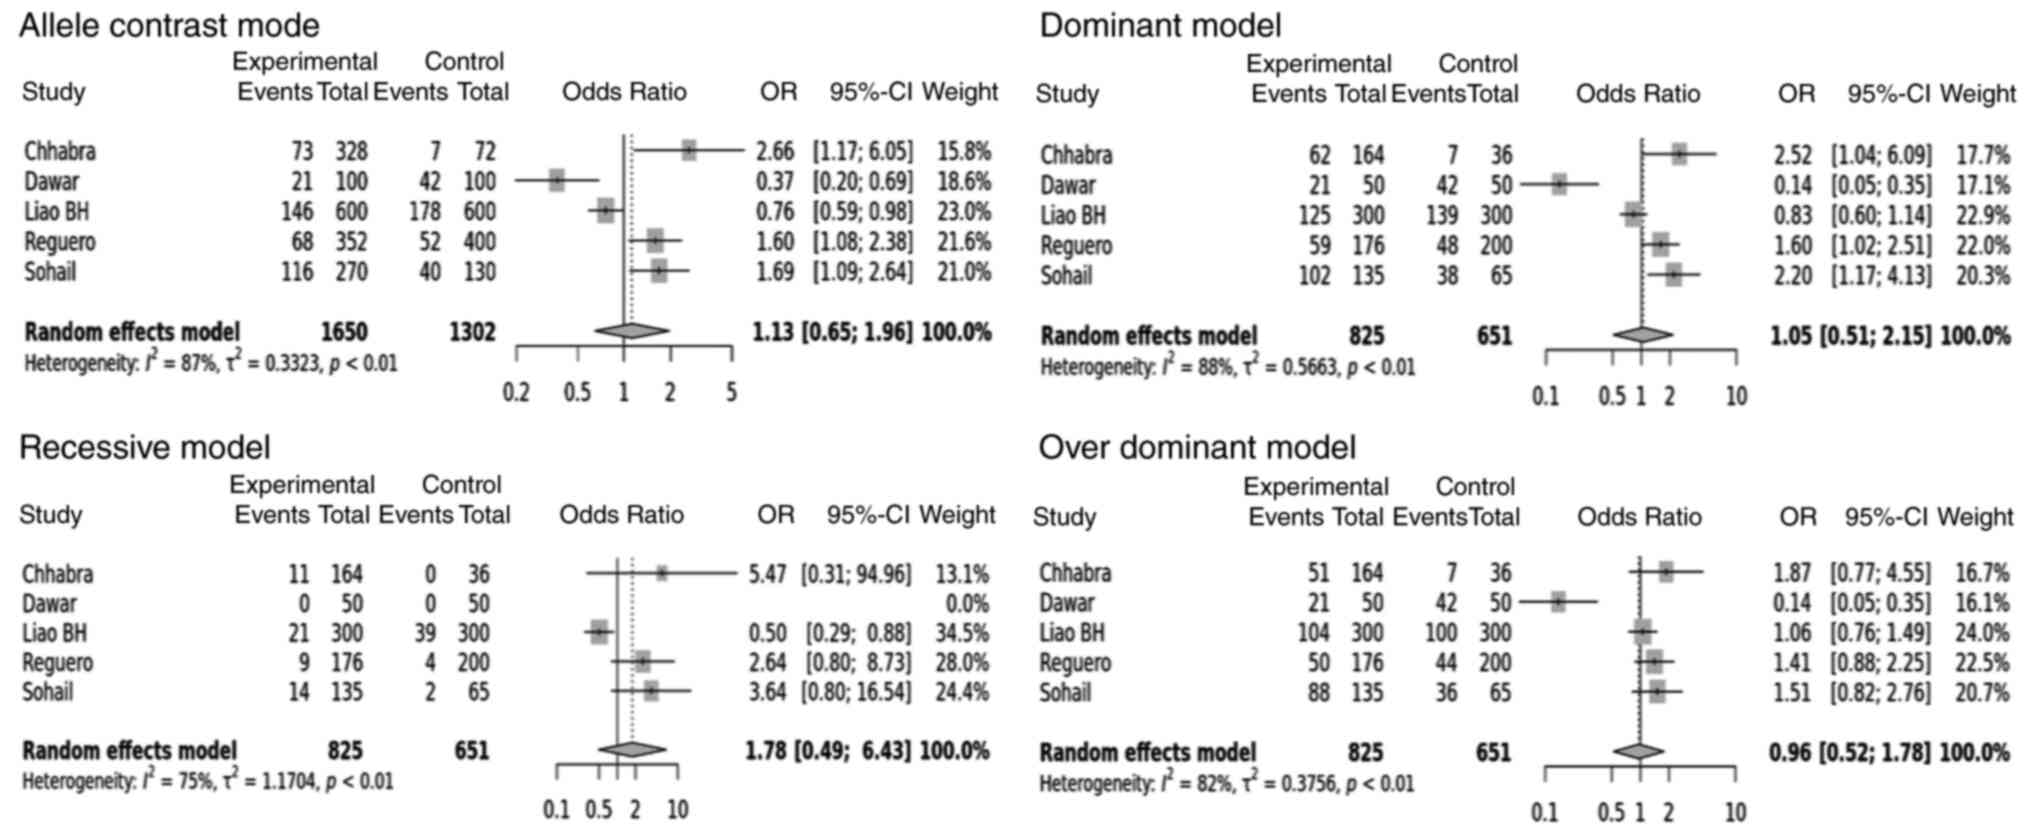
II). Under the allele contrast model, no statistically
significant association was identified using the random-effects
model (OR, 1.13; 95% CI, 0.65-1.96; P=0.675). Similarly, no
significant association was observed under the recessive model (OR,
1.78; 95% CI, 0.49-6.43; P=0.382), dominant model (OR, 1.05; 95%
CI, 0.51-2.15; P=0.904) and the over-dominant model (OR, 0.96; 95%
CI, 0.52-1.78; P=0.905) (Fig. 2).
To evaluate the influence of studies deviating from the HWE, an
additional sensitivity analysis was performed with only two studies
[Chhabra et al (15) and
Reguero et al (3)],
excluding the studies by Dawar et al (16), Liao et al (21) and Sohail et al (11). Following that, a statistically
significant association was observed under the allele contrast
model (OR, 1.81; 95% CI, 1.18-2.75; P=0.005) and dominant model
(OR, 1.75; 95% CI, 1.17-2.62; P=0.006). No significant association
was identified under the recessive model (OR, 2.94; 95% CI,
0.97-8.86; P=0.055) or over-dominant model (OR, 1.49; 95% CI,
0.98-2.26; P=0.056) (Table SII).
These findings suggest that studies deviating from the HWE may have
influenced the pooled estimates observed in the primary
analysis.
| Table IIGenotype distribution of rs670 with
HWE P-values. |
Table II
Genotype distribution of rs670 with
HWE P-values.
| | | | | Cases | Controls | | |
|---|
| Authors | Year of
publication | Country | Total no. of
cases/controls | GG | GA | AA | GG | GA | AA | HWE | (Refs.) |
|---|
| Chhabra et
al | 2005 | India | 164/36 | 102 | 51 | 11 | 29 | 7 | 0 | 0.5182 | (15) |
| Dawar et
al | 2010 | India | 50/50 | 29 | 21 | 0 | 8 | 42 | 0 | 0.0079 | (16) |
| Liao et
al | 2015 | China | 300/300 | 175 | 104 | 21 | 161 | 100 | 39 | 0.0005 | (20) |
| Reguero et
al | 1998 | Spain | 176/200 | 117 | 50 | 9 | 152 | 44 | 4 | 0.6983 | (3) |
| Sohail et
al | 2024 | Pakistan | 135/65 | 33 | 88 | 14 | 27 | 36 | 2 | 0.0156 | (11) |
High heterogeneity was found to be present in the
selected studies (I2=75 to 88%, P<0.01), suggesting
inconsistency across studies; this may be due to differences in
ethnicity, study design, sample size and outcomes across the
studies (Table III and Fig. 2) (3,11,15,16,21).
| Table IIIPooled OR and 95% CI values of the
association between APOA1 rs670 and risk of developing
cardiovascular disease. |
Table III
Pooled OR and 95% CI values of the
association between APOA1 rs670 and risk of developing
cardiovascular disease.
| rs670 genetic
model | Comparison | No. of studies | Pooled OR | 95% CI | Z-test P-value | Model | I2 | P-value
heterogeneity |
|---|
| Allele | A vs. G | 5 | 1.12 | 0.64-1.96 | 0.675 | Random effects
model | 86 | <0.001 |
| Dominant | AA/GA vs. GG | 5 | 1.04 | 0.50-2.15 | 0.904 | Random effects
model | 87 | <0.001 |
| Recessive | AA vs. GA/GG | 5 | 1.77 | 0.48-6.43 | 0.382 | Random effects
model | 75 | 0.0073 |
| Over-dominant | GA vs. GG/AA | 5 | 0.96 | 0.52-1.77 | 0.905 | Random effects
model | 81 | <0.001 |
The sensitivity analysis for APOA1 rs670, was
executed by removing one study at a time; this demonstrated that
the pooled effect remained mostly unaltered following the
sequential exclusion of each study, indicating that the observed
association was stable and not driven by any single study. A
summary of the meta-analysis of studies on rs670 is presented in
Table III.
Meta-analysis of APOA1 rs5069
A total of five studies were included to evaluate
rs5069 and their genotype distributions and HWE p-values are
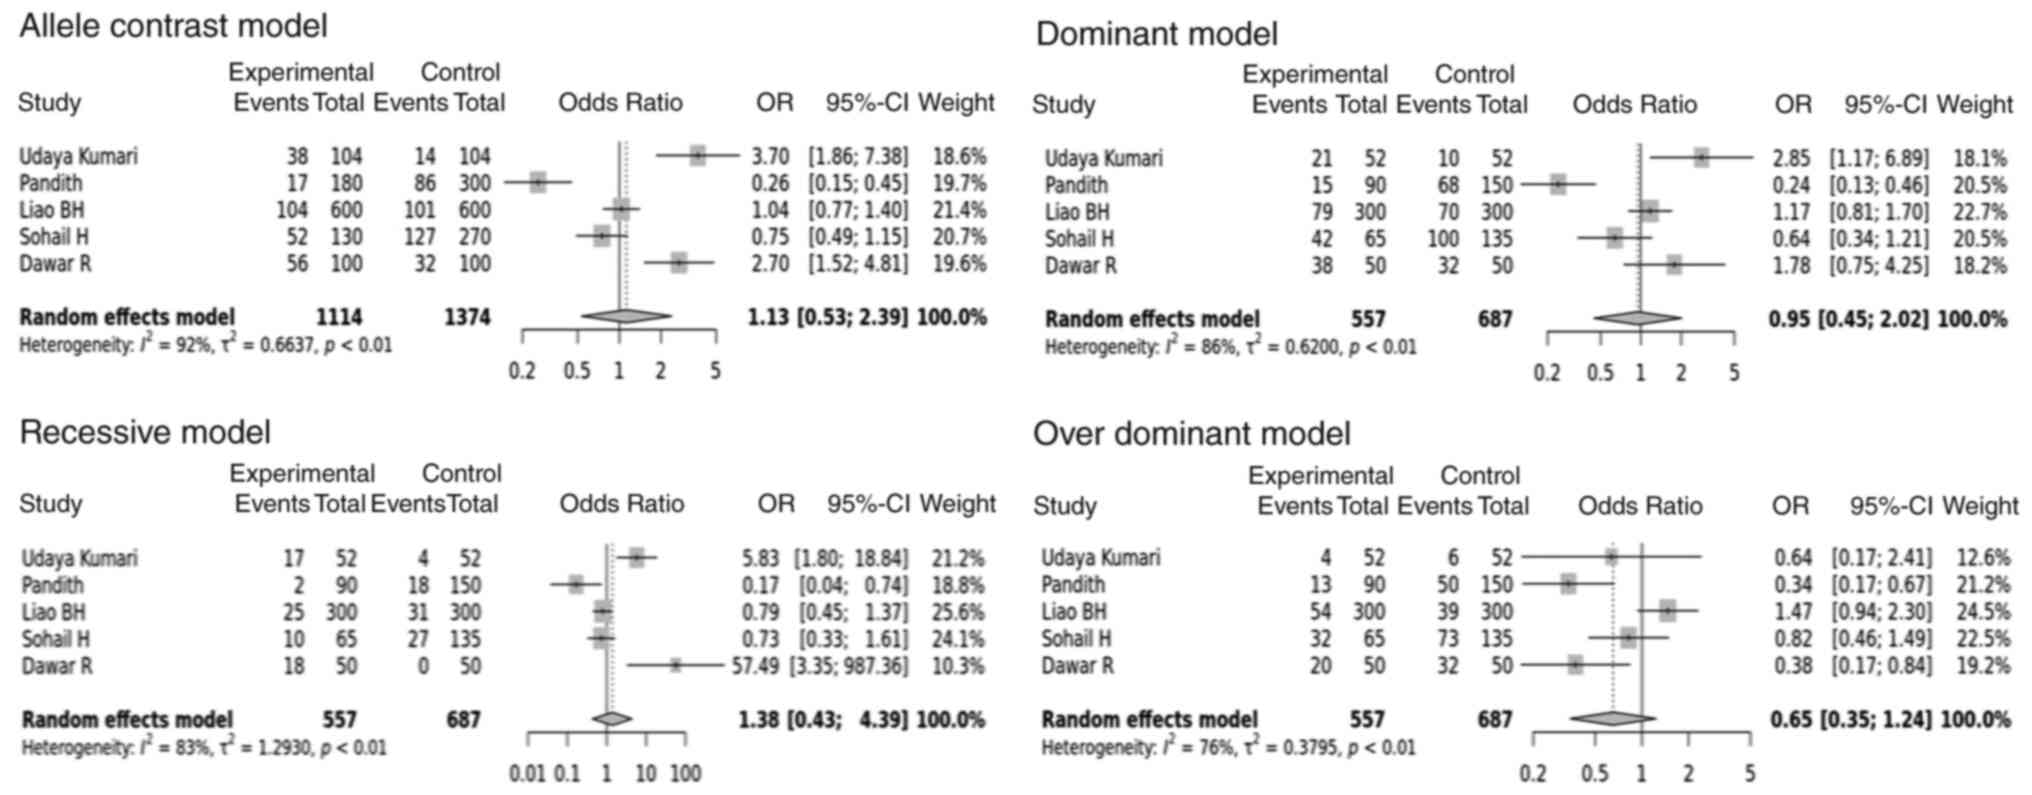
presented in (Table IV). No
statistically significant association was observed between rs5069
and disease susceptibility under the allele contrast model (OR,
1.13; CI, 0.53-2.39; P=0.752) using the random-effects model.
Similarly, no significant association was found under the dominant
(OR, 0.95; 95% CI, 0.45-2.02; P=0.892), recessive (OR, 1.38; 95%
CI, 0.43-4.39; P=0.590) and over-dominant (OR, 0.65; 95% CI,
0.35-1.24; P=0.192) models (Fig.
3). HWE sensitivity analysis was considered for APOA1 rs5069.
However, the exclusion of all studies whose control groups deviated
from HWE left only one eligible study for analysis. Therefore, a
pooled HWE-based sensitivity analysis could not be performed due to
insufficient data.
| Table IVGenotype distribution with HWE
P-value for rs5069. |
Table IV
Genotype distribution with HWE
P-value for rs5069.
| | | | | Cases | Controls | | |
|---|
| Authors | Year of
publication | Country | Total no. of
cases/controls | CC | CT | TT | CC | CT | TT | HWE | (Refs.) |
|---|
| Kumari et
al | 2023 | India | 52/52 | 31 | 4 | 17 | 42 | 6 | 4 | 0.0003 | (21) |
| Pandith et
al | 2021 | India | 90/150 | 75 | 13 | 2 | 82 | 50 | 18 | 0.0235 | (14) |
| Liao et
al | 2015 | China | 300/300 | 221 | 54 | 25 | 230 | 39 | 31 | 0 | (20) |
| Sohail et
al | 2024 | Pakistan | 65/135 | 23 | 32 | 10 | 35 | 73 | 27 | 0.3217 | (11) |
| Dawar et
al | 2010 | India | 50/50 | 12 | 20 | 18 | 18 | 32 | 0 | 0.0009 | (16) |
Substantial heterogeneity was present
(I2=92%; P<0.01) reflecting the effect of sizes
across the included studies (Table
V and Fig. 3) (11,14,16,17,21).
| Table VPooled OR and 95% CI values of the
association between APOA1 rs5069 and the risk of developing
cardiovascular disease. |
Table V
Pooled OR and 95% CI values of the
association between APOA1 rs5069 and the risk of developing
cardiovascular disease.
| Rs5069 Genetic
Model | Comparison | No. of studies | Pooled OR | 95% CI | Z-test P-value | Model | I² % | P-value
heterogeneity |
|---|
| Allele | T vs. C | 5 | 1.13 | 0.53-2.39 | 0.752 | Random effects
model | 92 | <0.001 |
| Dominant | TT/CT vs. CC | 5 | 0.95 | 0.44-02.02 | 0.892 | Random effects
model | 85.5 | <0.001 |
| Recessive | TT vs. CT/CC | 5 | 1.38 | 0.43-4.39 | 0.590 | Random effects
model | 83 | <0.001 |
| Over-dominant | CT vs. CC/TT | 5 | 0.65 | 0.34-1.23 | 0.192 | Random effects
model | 76 | <0.002 |
The sensitivity analysis for APOA1 rs5069 was
executed by removing one study at a time, demonstrating that the
pooled estimates did not materially change upon removal of
individual studies. A summary of the meta-analysis is presented in
Table V.
Publication bias
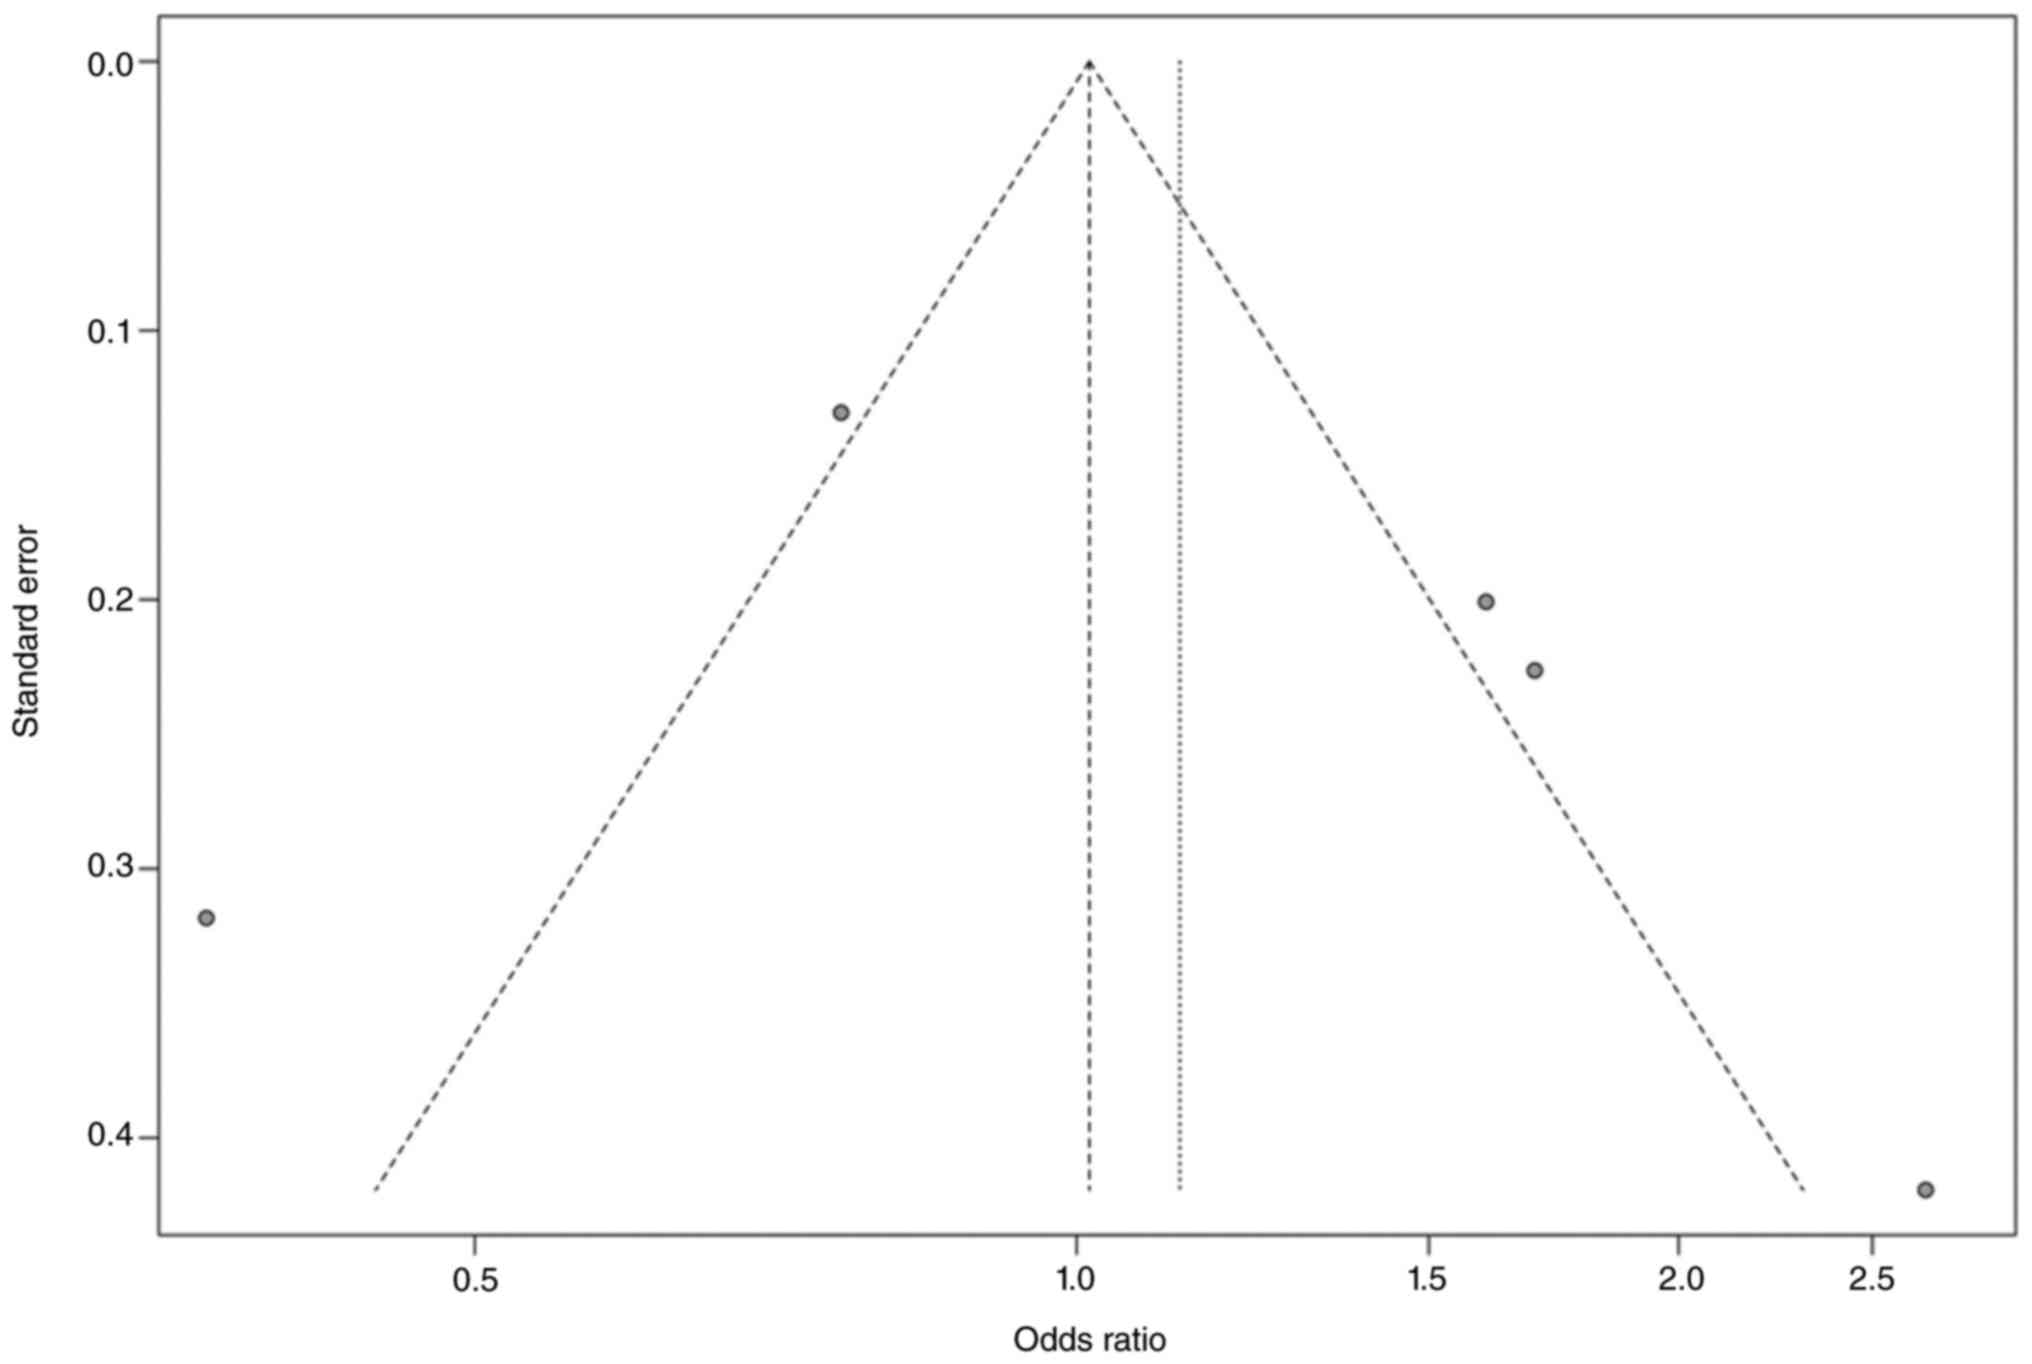
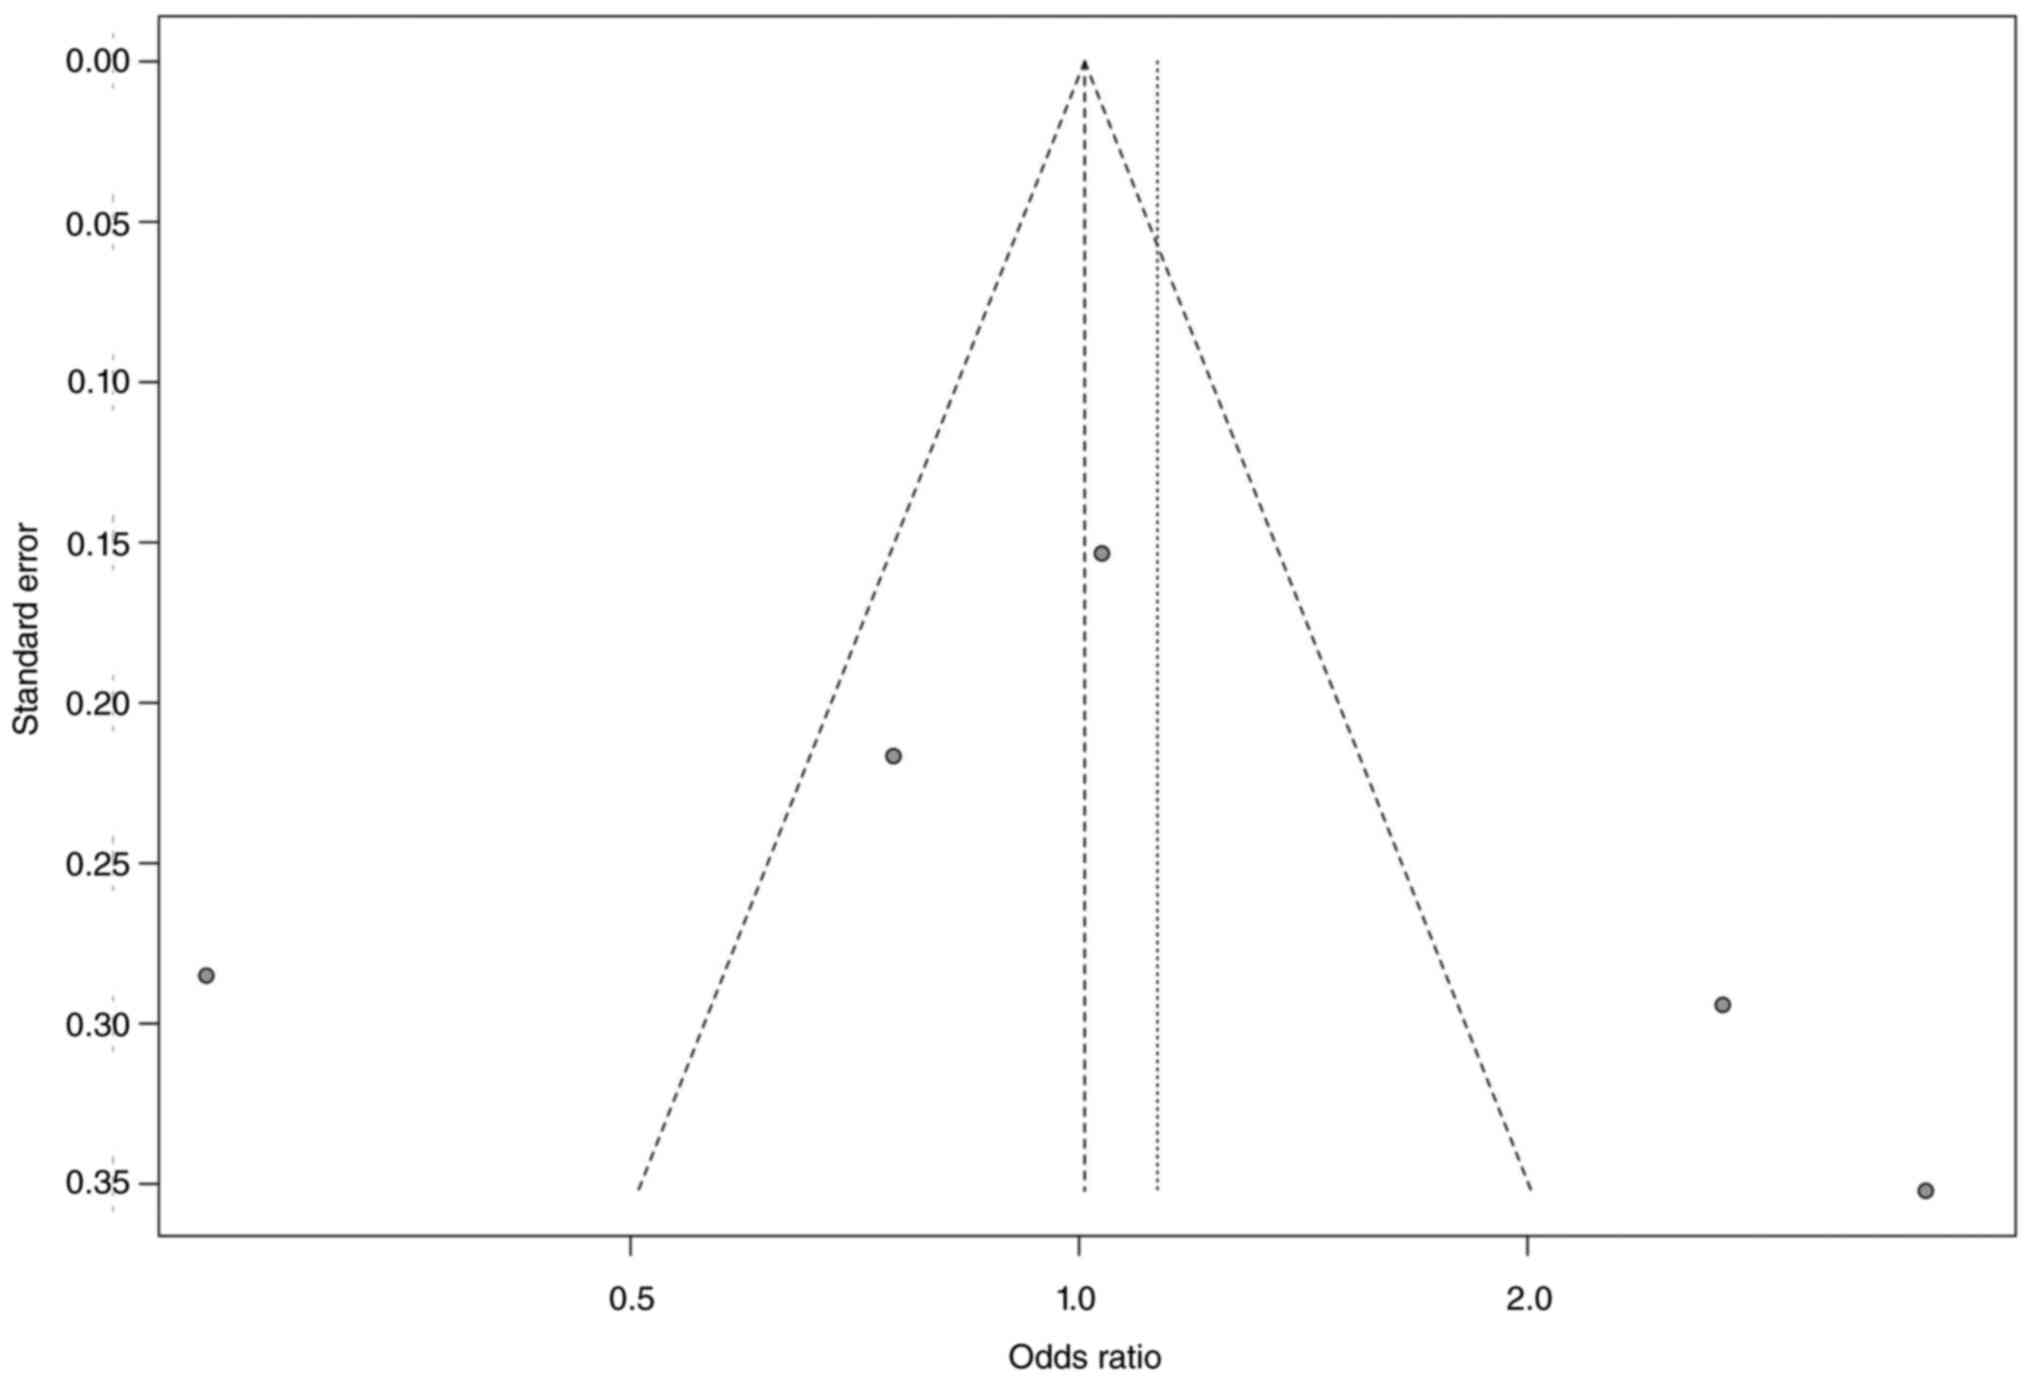
Publication bias was evaluated for both rs670 and
rs5069 by applying funnel plot and Egger's regressing test. The
funnel plots revealed mild asymmetry. However, only five studies
were available for each polymorphism; therefore, the statistical
power of these methods to detect publication bias was limited,
which should be interpreted cautiously. The funnel plots are
presented in Figs. 4 and 5.
Discussion
The present meta-analysis systematically evaluated
the association between the APOA1 rs670 and rs5069 polymorphisms
with susceptibility to CVD by pooling evidence from eligible
case-control studies published between 1998 to 2026. The
methodological quality of the studies was assessed using the NOS,
and all studies were of moderate to high quality. The pooled
analysis demonstrated that there was no statistically significant
association between the APOA1 rs670 polymorphism and susceptibility
CVD under the allele contrast, dominant, recessive and
over-dominant genetic models. Similarly, the APOA1 rs5069
polymorphism did not exhibit any significant association with the
risk of developing CVD under any of the evaluated genetic
models.
However, the HWE-based sensitivity analysis revealed
a significant association between the APOA1 rs670 polymorphism and
the risk of developing CVD under the allele contrast model and
dominant model following the exclusion of studies deviating from
the HWE. This finding suggests that HWE violations may have
contributed to the substantial heterogeneity observed in the
primary analysis. By contrast, for APOA1 rs5069, an HWE-based
sensitivity analysis was not feasible as the exclusion of studies
deviating from the HWE had left only one study for analysis.
Ethnicity-based subgroup analysis was also limited
as only one study included in the APOA1 rs670 analysis originated
from a European population (3),
while the remaining studies were conducted in Asian populations
(11,15,16,21).
Similarly, all studies included in the APOA1 rs5069 analysis were
derived from Asian populations (11,14,16,17,21).
Therefore, meaningful ethnicity-based subgroup analyses could not
be performed.
Overall, the findings of the present meta-analysis
did not reveal a statistically significant association between
APOA1 rs670 and APOA1 rs5069 with susceptibility to CVD in the
pooled analysis. However, previous studies have reported that the
APOA1 rs670 and APOA1 rs5069 polymorphisms may influence lipid
parameters in certain populations (17,21).
However, the sensitivity analysis based on HWE indicated
significant association between the rs670 polymorphism and the risk
of developing CVD under specific genetic models, suggesting that
this variant may contribute to disease susceptibility under certain
conditions. However, no conclusion could be drawn for rs5069 due to
limited data.
Xu et al (13) and Dong et al (12) evaluated the association between the
APOA1 polymorphism and CAD. However, the present meta-analysis
implemented an overall CVD approach by including studies
investigating multiple cardiovascular outcomes including CAD, MI
and ACS. Therefore, the present meta-analysis provides a
comprehensive assessment of the APOA1 rs670 and rs5069
polymorphisms associated with susceptibility to CVD overall, rather
than a single phenotypic characteristic. Furthermore, the present
study incorporated recent evidence published up to 2026 providing
updated synthesis of available literature.
Substantial heterogeneity was observed across the
included studies. This variable may be explained by difference in
ethnicity, sample size, cardiovascular disease phenotype,
genotyping methods, environmental exposure and study design. The
sensitivity analysis of studies on APOA1 rs670 demonstrated that
the pooled estimates remained relatively stable by excluding
individual studies, suggesting that no single study substantially
influenced the overall findings.
The present meta-analysis has several strengths. It
provides an updated analysis of available evidence by including
recently published studied and systematically evaluated two
commonly investigated APOA1 polymorphisms using multiple genetic
models. The performance of sensitivity analysis, HWE assessment has
enhanced the robustness od the findings.
However, the present meta-analysis has several
limitations which should be considered when interpreting the
findings. First, the number of included studies was relatively
small, which may have limited the statistical power of pooled
analysis. Second, substantial heterogeneity was observed across
studies, potentially reflecting difference in ethnicity, study
design, sample size, cardiovascular outcomes, and genotyping
methods. Third, potential gene-gene and gene-environment
interactions could not be evaluated due to insufficient data and
inadequate reporting of environmental exposures in the included
studies. Finally, publication bias assessment should be interpreted
cautiously as fewer than ten studies where available for each
polymorphism, limiting the reliability of funnel plot and Egger's
test results.
In conclusion, the present meta-analysis found no
significant association between the APOA1 rs670 and rs5069
polymorphisms and the overall risk of developing CVD in the primary
pooled analyses under any genetic model. However, substantial
heterogeneity was observed across studies. Notably, HWE-based
sensitivity analysis for rs670 revealed a significant association
under the allele contrast and dominant models. However, such an
analysis for rs5069 was not feasible due to limited data. Overall,
these findings should be interpreted cautiously and further studies
are warranted to confirm these findings and provide further
insight.
Supplementary Material
Methodological quality assessment of
the included studies using the Newcastle-Ottawa Scale.
Sensitivity analysis of the APOA1
rs670 polymorphism following the exclusion of studies deviating
from the Hardy-Weinberg equilibrium.
Acknowledgements
The authors would like to thank the Chettinad
Academy of Research and Education (Kelambakkam, India) for
providing the institutional facilities and literature databases
required to conduct the present study.
Funding
Funding: No funding was received.
Availability of data and materials
The data generated in the present study may be
requested from the corresponding author.
Authors' contributions
HN and SG conceptualized the study. HN was involved
in the study methodology, MetaGenyo software for genetic
association meta-analysis provision, resources of literature
databases, data curation, in the writing of the original draft of
the manuscript, and in the writing, reviewing and editing of the
manuscript. SG was involved in the formal analysis and
investigative aspects of the study. SG were involved in data
validation, visualization, supervision, project administration. HN
and SG confirm the authenticity of all the raw data. Both authors
have read and approved the final manuscript.
Ethics approval and consent to
participate
Not applicable.
Patient consent for publication
Not applicable.
Competing interests
The authors declare that they have no competing
interests.
Use of artificial intelligence tools
During the preparation of this work, AI tools
(ChatGPT) were used to improve the readability and language of the
manuscript or to generate images, and subsequently, the authors
revised and edited the content produced by the AI tools as
necessary, taking full responsibility for the ultimate content of
the present manuscript
References
|
1
|
Kim SJ, Mesquita FCP and Hochman-Mendez C:
New biomarkers for cardiovascular disease. Tex Heart Inst.
50(e238178)2023.PubMed/NCBI View Article : Google Scholar
|
|
2
|
Tada H, Fujino N, Hayashi K, Kawashiri MA
and Takamura M: Human genetics and its impact on cardiovascular
disease. J Cardiol. 79:233–239. 2022.PubMed/NCBI View Article : Google Scholar
|
|
3
|
Reguero JR, Cubero GI, Batalla A, Alvarez
V, Hevia S, Cortina A and Coto E: Apolipoprotein A1 gene
polymorphisms and risk of early coronary disease. Cardiology.
90:231–235. 1998.PubMed/NCBI View Article : Google Scholar
|
|
4
|
World Health Organization (WHO):
Cardiovascular diseases. WHO, Geneva, 2026. https://www.who.int/health-topics/cardiovascular-diseases#tab=tab_1.
|
|
5
|
Janani J, Lakshmanan K and Gopalakrishnan
S: Unveiling the atherogenic lipoprotein particle: A case-control
study. Rom J Diabetes Nutr Metab Dis. 30:398–402. 2023.
|
|
6
|
Padró T, Vilahur G and Badimon L:
Dyslipidemias and microcirculation. Curr Pharm Des. 24:2921–2926.
2018.PubMed/NCBI View Article : Google Scholar
|
|
7
|
Ordovas JM: Genetic influences on blood
lipids and cardiovascular disease risk: Tools for primary
prevention. Am J Clin Nutr. 89:1509S–1517S. 2009.PubMed/NCBI View Article : Google Scholar
|
|
8
|
Chen ES, Mazzotti DR, Furuya TK,
Cendoroglo MS, Ramos LR, Araujo LQ, Burbano RR and de Arruda
Cardoso Smith M: Apolipoprotein A1 gene polymorphisms as risk
factors for hypertension and obesity. Clin Exp Med. 9:319–325.
2009.PubMed/NCBI View Article : Google Scholar
|
|
9
|
Jomard A and Osto E: High density
lipoproteins: Metabolism, function, and therapeutic potential.
Front Cardiovasc Med. 7(39)2020.PubMed/NCBI View Article : Google Scholar
|
|
10
|
Ghaemi F, Emadzadeh M, Almahmeed W,
Jamialahmadi T, Karav S and Sahebkar A: ApoA1/HDL-C ratio as a
predictor for coronary artery disease in patients with type 2
diabetes: A matched case-control study. BMC Cardiovasc Disord.
24(317)2024.PubMed/NCBI View Article : Google Scholar
|
|
11
|
Sohail H, Shahzad M, Khaliq S and Ijaz F:
Lipoprotein oxidation, genetic expression and polymorphism of Apo A
and B gene in patients with coronary artery disease in a Pakistani
Punjabi population. Sains Malays. 53:1185–1199. 2024.
|
|
12
|
Dong LP, Huang D and Cai WJ: Meta-analysis
of the association between Apo-A1 rs670, rs5069 polymorphisms and
coronary artery diseases. Int J Clin Exp Med. 11:6445–6453.
2018.
|
|
13
|
Xu LB, Zhou YF, Yao JL, Sun SJ, Rui Q,
Yang XJ and Li XB: Apolipoprotein A1 polymorphisms & risk of
coronary artery disease: A meta-Analysis. Arch Med Sci. 13:813–819.
2017.PubMed/NCBI View Article : Google Scholar
|
|
14
|
Pandith AA, Bhat IA, Niyaz I, Qasim I,
Bhat IA, Manzoor U and Koul AM: Association of APOA1-75G/A and
+83C/T polymorphic variation with acute coronary syndrome patients
in Kashmir (India). J Cardiovasc Thorac Res. 13:109–115.
2021.PubMed/NCBI View Article : Google Scholar
|
|
15
|
Chhabra S, Narang R, Lakshmy R and Das N:
APO A1-75 G to A substitution associated with severe forms of CAD,
lower levels of HDL and ApoA-I among Northern Indians. Dis Markers.
21:169–174. 2005.PubMed/NCBI View Article : Google Scholar
|
|
16
|
Dawar R, Gurtoo A and Singh R:
Apolipoprotein A1 gene polymorphism (G-75A and C+83T) in patients
with myocardial infarction: A pilot study in a North Indian
population. Am J Clin Pathol. 134:249–255. 2010.PubMed/NCBI View Article : Google Scholar
|
|
17
|
Kumari GU, Preethi A, Talikoti P,
Balasubramanian A, Devi CA, Vinodha J, Rekha K and Vijayalakshmi M:
Association of single nucleotide polymorphism of Apo A-1 gene and
lipid variables in patients with myocardial infarction: A
case-control study. Natl J Lab Med. 12:BO01–BO05. 2023.
|
|
18
|
Wells GA, Shea B, O'Connell D, Peterson J,
Welch V, Losos M and Tugwell P: The Newcastle-Ottawa Scale (NOS)
for assessing the quality of nonrandomised studies in
meta-analyses. Ottawa Hospital Research Institute. https://ohri.ca/en/who-we-are/core-facilities-and-platforms/ottawa-methods-centre/newcastle-ottawa-scale.
|
|
19
|
Martorell-Marugan J, Toro-Domínguez D,
Alarcón-Riquelme ME and Carmona-Saez P: MetaGenyo: A web tool for
meta-analysis of genetic association studies. BMC Bioinformatics.
18(563)2017.PubMed/NCBI View Article : Google Scholar
|
|
20
|
Velmurugan S, Pauline R and Subbaraj GK:
Association of candidate gene (INSR & THADA)
polymorphism with polycystic ovary syndrome: Meta-analysis and
statistical power analysis. J Turk Ger Gynecol Assoc. 25:167–178.
2024.PubMed/NCBI View Article : Google Scholar
|
|
21
|
Liao BH, Cheng KQ, Dong SH, Liu HD and Xu
ZL: Effect of apolipoprotein A1 genetic polymorphisms on lipid
profiles and the risk of coronary artery disease. Diagn Pathol.
10(102)2015.PubMed/NCBI View Article : Google Scholar
|